
Vitrectomy recovery: a week-by-week guide
Most people gradually return to everyday activities over the first days and weeks after vitrectomy. Vision usually follows a slower timetable, often improving over weeks or months. The reason for your operation, the health of your retina and whether you have a gas bubble all affect recovery.

Published
This guide helps you plan life at home. Your own written instructions take priority, especially for eye drops, head positioning and follow-up appointments.
When should I seek urgent help?
Contact your surgical team immediately if you develop:
- Severe or increasing eye pain.
- A sudden drop in vision, a new dark curtain or shadow, new flashes, or a sudden shower of floaters.
- Increasing redness, particularly with pain or worsening vision, or concerning discharge.
- Eye pain with a bad headache, nausea or vomiting.
Do not assume a new problem is simply the gas bubble or normal healing. Do not wait for your next appointment.
Why does recovery vary so much?
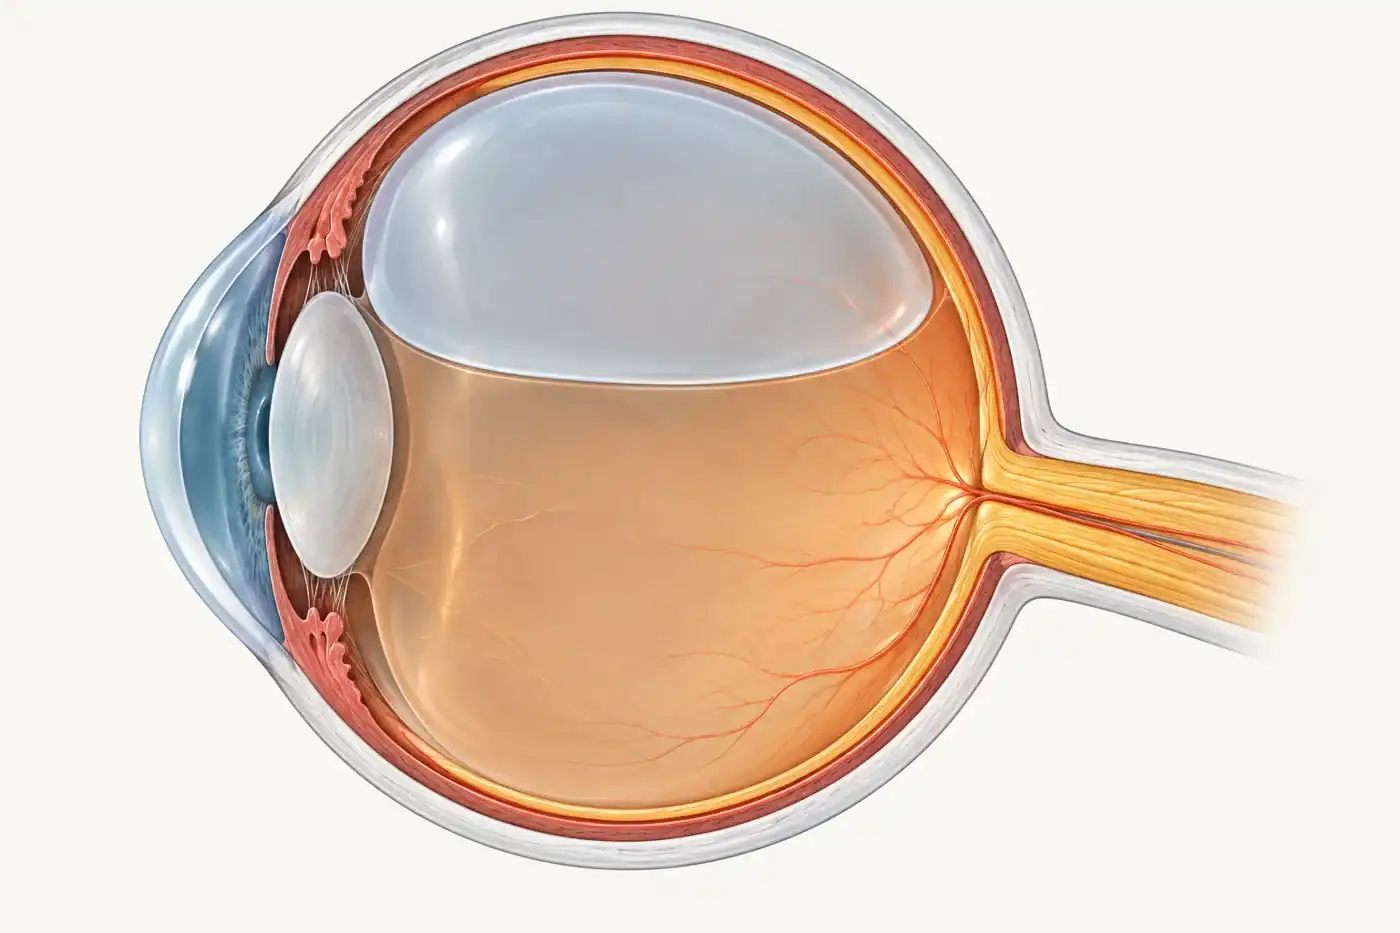
Vitrectomy removes the vitreous gel from inside the eye so the surgeon can treat a problem affecting the vitreous or retina. The small surface wounds may become comfortable well before the retina has finished recovering.
Three details shape your plan:
- What was treated. Removing an epiretinal membrane, closing a macular hole and repairing a retinal detachment can involve different recovery needs.
- What was left inside the eye. Fluid, air, a longer-lasting gas or silicone oil may be used. Not every vitrectomy involves a gas bubble.
- Whether positioning is needed. Some people need to keep their head in a particular position to support the repair; others do not.
The condition of the retina before surgery also matters. A successful repair does not always restore all the vision that was lost.
What does recovery look like at a glance?
This table summarises what to expect at each stage and what usually helps. It is a general guide: the operation you had, whether gas or oil was used and your own instructions take priority.
| When | What you may notice | What to do |
|---|---|---|
| 1First 24–48 hours |
|
|
| 2Rest of the first week |
|
|
| 3Weeks two to four |
|
|
| 4Four to six weeks |
|
|
| 5Beyond six weeks |
|
|
At any stage, contact your surgical team immediately for severe or increasing pain, a sudden drop in vision, a new curtain or shadow, or new flashes or floaters.
What should I organise before going home?
Arrange someone to collect you, help with the journey and follow the hospital's instructions about staying with you after sedation or anaesthesia. Prepare simple meals and arrange help with lifting, shopping, childcare or other tasks you may be unable to do straight away.
Before discharge, make sure you know:
- Whether your eye contains fluid, air, gas or silicone oil, and the gas name if one was used.
- Which drops to use, when to start them and whether the schedule changes over time.
- Any head-positioning instructions, including sleep, breaks and how many days to continue.
- When to remove the initial dressing and how long to wear your protective shield.
- When and where your next examination will be, and who to contact urgently.
Keep these instructions somewhere easy to find. If reading small print is difficult, ask for a larger copy or have someone help with a clear medication schedule. Arrange transport for follow-up visits as well as the journey home.
What happens in the first 24–48 hours?
Expect to take things quietly while you settle into the drop and positioning routine. Your eye may feel gritty, watery or mildly sore. Vision can be blurred, particularly if a gas bubble is present. The degree of blur alone does not tell you whether the retinal repair has worked.
Use only the pain relief recommended for you and follow its instructions. Severe pain, increasing pain or pain that is not settling needs advice; it is not something to push through.
Keep the initial dressing on for the period specified at discharge. Once it is removed, avoid rubbing or pressing on the eye. Dr Chen's usual advice is to wear the protective shield at night for four nights, unless your own instructions differ.
Poor vision in one eye can make judging steps, distances and pouring drinks awkward. Good lighting, clear walkways and help with unfamiliar stairs can make the first few days easier. Do not drive yourself to an early review.
What can I do during the rest of the first week?
Build a manageable routine around your prescribed drops, any positioning and short periods of comfortable activity. Gentle walking is usually suitable if you can see well enough to move safely and can keep to your positioning instructions.
Reading, watching television and using a phone or computer are safe to do and will not damage the retinal repair. Start with short sessions, enlarge the text and take breaks if the eye feels uncomfortable. If positioning is prescribed, choose an activity that fits that position rather than changing your head position to see the screen.
Avoid rubbing the eye, heavy lifting and dusty or dirty tasks. Arrange help rather than testing what you can lift. Mild discomfort should become easier; new or worsening symptoms need assessment.
You may feel ready to do more before your vision is useful for every task. Being comfortable enough to watch television does not mean you are ready to drive, exercise hard or return to a hazardous job.
What changes during weeks two to four?
Many people can gradually do more around the house or return to suitable work during this period. Avoid heavy lifting for the first two weeks under Dr Chen's usual instructions, and check before restarting strenuous exercise or demanding physical work. Reaching the two-week mark is not automatic clearance for every activity.
Keep taking drops for the prescribed course, including any gradual reduction. Do not stop because the eye looks better, and do not continue a bottle indefinitely without checking the plan.
If there is gas in your eye, it may still substantially limit vision and travel. A longer-lasting bubble can remain well beyond the first month. People without gas may regain useful day-to-day vision sooner, but the underlying retinal condition still determines the longer-term result.
Keep every planned review even if recovery seems straightforward. The examination checks the retinal repair, healing and eye pressure, which you cannot reliably judge at home.
Should my vision be back to normal by six weeks?
Not necessarily. Six weeks is a useful point to review progress, not a deadline for full recovery. Improvement after macular surgery or retinal detachment repair can continue for months. Some distortion, blur or loss of detail may remain because of the original retinal damage.
A gas bubble can delay clear vision. Silicone oil can also affect sight and may need a later operation to remove it; the timing is individual. Oil does not dissolve in the same way as gas.
Dr Chen generally advises waiting at least four weeks before arranging new glasses, and longer if the bubble remains or the prescription is still changing. Ask when your eye is ready to be measured rather than buying new lenses simply because four weeks have passed.
If you still have your natural lens, a cataract may progress after vitrectomy and cause later blur. Read more about cataract surgery after vitrectomy. A change in vision still needs assessment rather than being assumed to be cataract.
What will a gas bubble look like as it disappears?
Gas acts as a temporary internal support for some retinal repairs. It is gradually absorbed and replaced by fluid made by the eye.
At first, a large bubble can make sight very poor. Many people say it is like looking through swimming goggles filled with water. As the gas is absorbed, a curved line appears towards the top of your vision, rather like the bubble in a spirit level, and it wobbles as you move. The line sinks lower as the bubble shrinks. Once it drops below your line of sight, the view above it is usually much clearer.
As the bubble shrinks further, the line curves more and more until it becomes a circle. In the last few days before the gas disappears, it looks like a small round ball in the lower part of your vision that moves around as you move your eye.
That familiar, changing boundary is different from a new fixed curtain, sudden loss of vision or increasing pain. If you are unsure whether what you see is expected, contact the team.
As a rough guide, Dr Chen advises that SF6 gas often lasts about two weeks and C3F8 about six weeks. These are estimates, and gas can last longer. The amount and type used affect the timing. Do not use the expected disappearance date to decide whether it is safe to fly.
Can I fly, travel to the mountains or have another anaesthetic?
Do not fly while any air or gas remains in your eye, even a small bubble. Reduced air pressure can enlarge the bubble and dangerously raise pressure inside the eye. Your surgeon needs to confirm that the gas is gone and that you can travel safely.
Ask before travelling to higher altitude by road as well. A mountain trip can involve a significant change in pressure without an aeroplane journey. Discuss planned travel before surgery where possible.
Nitrous oxide must not be used while gas remains in the eye. It can rapidly expand the bubble and threaten vision. It may be offered during anaesthesia, dental care or emergency pain relief, sometimes under the names “laughing gas” or “gas and air”.
Tell every treating clinician that you have an eye gas bubble, including ambulance staff, dentists and anaesthetists. Keep any gas warning card or wristband provided by the hospital. Other care can still be arranged using appropriate alternatives.
If you have silicone oil rather than gas, ask for advice specific to your eye. Do not assume that another person's travel instructions apply to you.
Will I need face-down positioning, and how should I sleep?
Only follow a face-down routine if your surgical team prescribes it. The correct position may be face down, on a particular side or another position, depending on the operation. There is no single schedule that suits every retinal repair.
Ask the team to demonstrate your position and write down how it applies during the day, at night and during breaks. Do not assume that being allowed to sit up during a break means you can sleep in any position.
A suitable support can make positioning more manageable. Have someone help arrange meals, drinks, audio entertainment and any equipment before you need them. Keep the setup comfortable without pressing on the operated eye.
Tell the team before surgery if neck or back problems, breathing difficulties or another condition may make positioning difficult. If you cannot manage the prescribed routine, or develop significant discomfort or numbness, contact the team so they can help you adapt it safely.
Positioning after retinal surgery: a practical guide

How do I manage drops, washing and everyday activities?
How should I put in my eye drops?
Wash your hands first and avoid touching the bottle tip to your eye, eyelashes or skin. Follow the written schedule for each bottle. Ask the nurse to demonstrate the technique if you are unsure, particularly if you also have positioning instructions.
A simple tick list or phone reminder can help. If you cannot manage the bottles, arrange help. Contact the clinic or pharmacist about a missed dose, an unexpected reaction or unclear instructions rather than guessing how to change the treatment.
Can I shower and wash my hair?
Usually you can wash carefully, but keep soap, shampoo and direct water spray out of the operated eye. Avoid rubbing it dry. Arrange help with hair washing if needed, and keep to any prescribed head position. Follow the discharge advice about how long to protect the eye from water.
When can I swim, wear eye make-up or garden?
Wait until the surgical team says these activities are suitable. Swimming exposes the eye to water; make-up removal can involve rubbing; gardening can expose it to dirt or injury. The appropriate interval depends on healing and your operation. Ask for a specific date or review point rather than borrowing a timetable from cataract surgery.
Can I bend down or exercise?
There is no single rule for every vitrectomy. Follow your positioning instructions and avoid heavy lifting or straining in the early recovery period. Ask about the actual task you want to resume — carrying a child, weight training or gardening — so the advice fits your situation. Start more demanding exercise only when cleared.
When can I return to work and driving?
Time off work can range from about two days to two weeks, depending on the condition treated and the work involved. Some people need longer, particularly with positioning, persistent poor vision or physically demanding duties.
A short period of desk work at home is different from a full day commuting, lifting, operating machinery or working at heights. Discuss duties, travel and the possibility of shorter hours or lighter work. A medical certificate can reflect the recovery plan rather than a standard number of days.
Do not drive while a gas bubble remains. After it disappears, you still need adequate vision and advice that it is safe to resume. Vision in the other eye, depth perception and any distortion matter too. Feeling comfortable or reaching a particular week is not enough. Arrange alternative transport until you have been assessed.
What should I ask at my follow-up appointment?
Bring your drops and instructions, along with questions about the activities you want to restart:
- Is the retina healing as expected, and what might still limit my vision?
- Is there any gas left, and do my positioning or sleeping instructions change?
- Should any drops change or stop?
- Can I return to my usual work, exercise and driving?
- When can I travel, swim or arrange new glasses?
Use the week-by-week guide to organise support and everyday life, while allowing your own examinations and recovery plan to guide the next step.
Sources and further reading
- American Society of Retina Specialists — Vitrectomy .
- Hull University Teaching Hospitals — Vitrectomy surgery .
- Oxford University Hospitals — Following vitreoretinal surgery .
- Royal Free London — Vitrectomy surgery .
- Royal College of Ophthalmologists — Safety alert about nitrous oxide and gas in an operated eye .
- Moorfields Eye Hospital — Macular hole treatment and gas precautions .