
Negative dysphotopsia: a dark shadow after cataract or lens surgery
Negative dysphotopsia is a dark crescent or curved shadow near the outer edge of vision that some people notice after cataract surgery or lens replacement. It is thought to involve the way light travels through and around the edge of the lens implant, but the exact mechanism remains debated. Many early symptoms fade; persistent, troublesome symptoms can sometimes be helped by further treatment.

Published
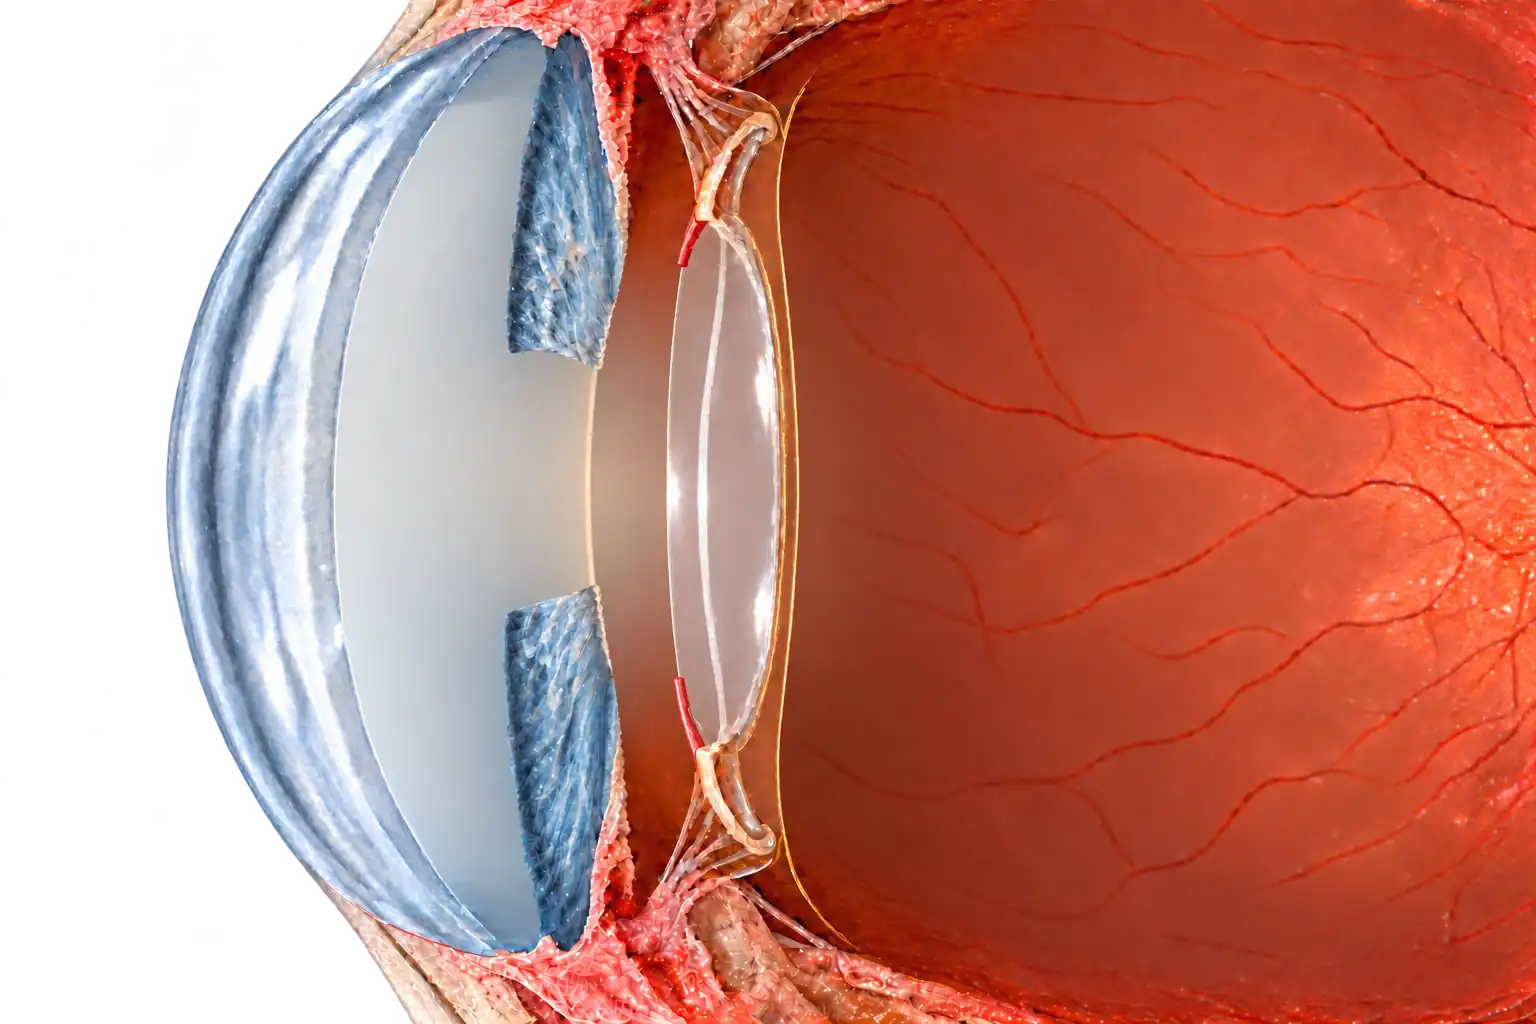
- Iris
- Zonules
- Haptic
- Lens implant optic
- Edge of the anterior capsule opening
- Anterior capsule overlapping the optic edge
- Posterior capsule
When does a shadow need urgent attention?
Seek urgent eye assessment for a new or worsening shadow, a curtain across your vision, new flashes or floaters, or reduced vision. It is important to be assessed to identify or exclude a retinal detachment which can cause a painless shadow that resembles negative dysphotopsia.
What does negative dysphotopsia look like?
The shadow is usually on the temporal side of the visual field: towards the right temple for the right eye, or the left temple for the left eye. People may describe a dark arc, a crescent or the impression of a spectacle frame when no glasses are being worn. Some people compare it to the view past a horse's blinkers. It may be more noticeable in bright conditions or particular directions of lighting. Central vision can remain clear, including when reading an eye chart.
“Negative” means a dark or missing-light phenomenon. “Positive dysphotopsia” describes added light effects such as bright arcs, glare or streaks. The two can coexist, but their explanations and treatment are not interchangeable.
Negative dysphotopsia simulation
Choose an eye and adjust the shadow strength. The scene represents what the person sees, so the right-eye shadow appears on the right of the picture. The shape, position and darkness vary between people; some notice a narrow bright area beyond the dark arc.
 Right eye · outer right side
The slider changes how dark the shadow is. Illustration only.
Why might the edge of the implant create a shadow?
The edge matters because it is a boundary between two different routes for light. Some light passes through the implant and is bent by it; very oblique light may pass outside its edge. The iris, pupil and thin capsule holding the implant affect which rays can take each route. The leading theories concern how those rays illuminate the far peripheral retina. They do not require the implant to have an opaque or damaged rim.
The retina is the light-sensitive lining at the back of the eye. An effect on its nasal side, towards the nose, is perceived in the opposite, temporal side of the visual field. This reversal is why the suspected retinal illumination gap and the shadow you notice are on opposite sides.
The implant normally sits inside the remaining lens capsule. The opening in the front of the capsule may be smaller than the implant's clear central optic, leaving a thin rim over its edge.
Could there be a gap between two areas of light?
The illumination-gap theory is a leading explanation. Light bent through the implant and light travelling outside its edge may reach different parts of the peripheral retina, with a less illuminated strip between them. That strip may be perceived as a dark crescent. The effect depends on the eye's anatomy and the implant's optical properties, rather than one lens feature alone. Optical models support the theory, but do not explain every case.
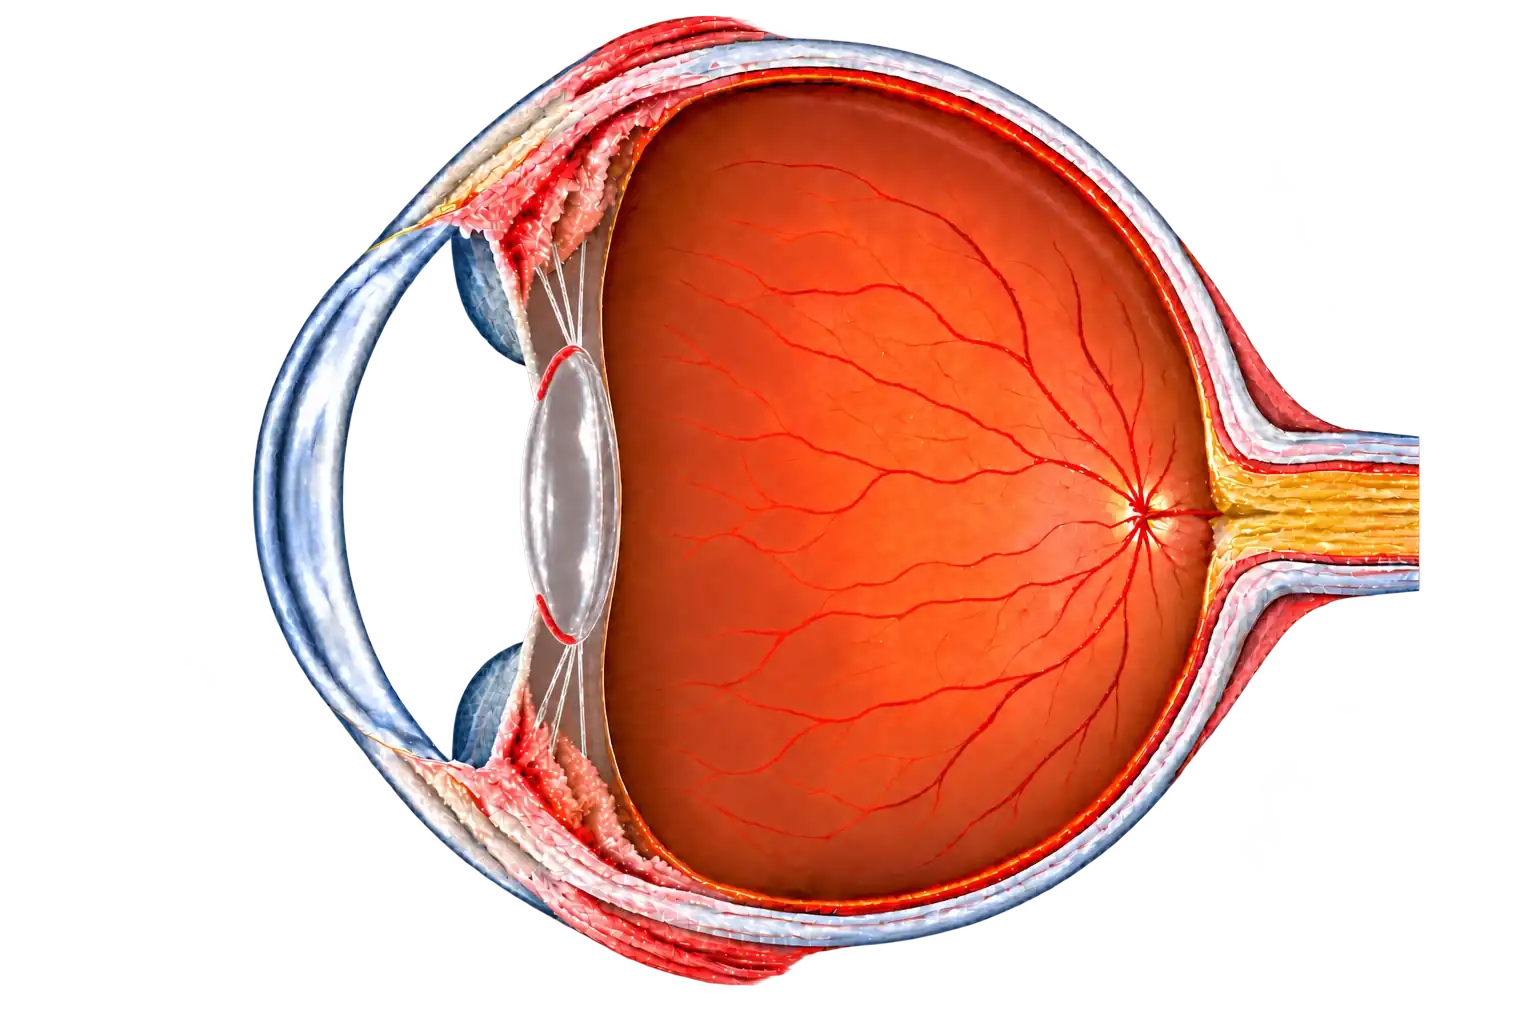
- Light bent through the implant
- Light passing outside the implant
- Iris
- Lens implant
- Retina
- Strip receiving less light
How could the iris and pupil contribute?
The iris is a three-dimensional structure, not a paper-thin aperture. Its thickness and shape can screen out very oblique light, much like the edge of a camera aperture. Researchers call this vignetting. Pupil size and position, and the gap between the iris and implant, also influence which rays pass through the optic and which miss it. These factors may alter whether an illumination gap becomes visible.
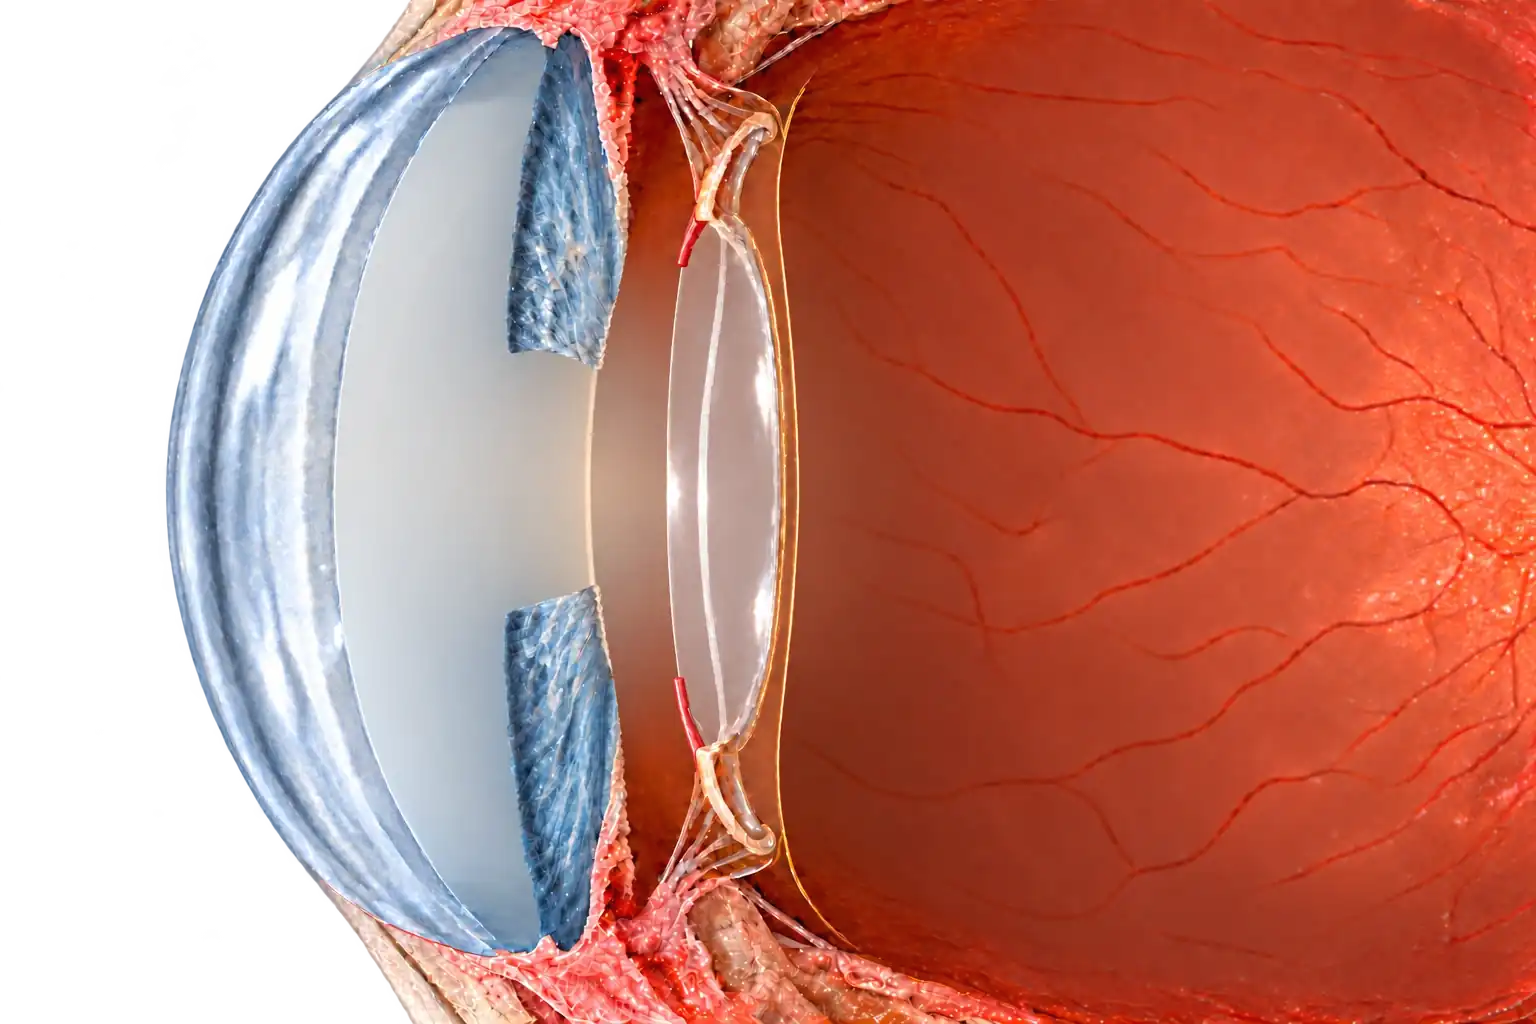
- Blocked by the iris
- Light through the pupil and implant
- Pupil
- Iris
- Posterior capsule
Could the capsule rim play a part?
The front capsule, particularly its nasal rim, may interact with the optic edge and change peripheral illumination. Some patients improve when the implant's optic is moved in front of that rim, or when a supplementary lens is placed in front of the original implant. This supports a role for the capsule–optic relationship, although it does not prove a single mechanism.
Other proposed contributors include temporary swelling around the corneal incision, especially in the early post-operative period, and changes in visual processing as the brain adapts to the new optics. Healing of the capsule may also change how light is scattered. More than one factor may be involved. Adaptation is a possible explanation for improvement.
Does it mean something went wrong with surgery?
No. Negative dysphotopsia is typically reported after uncomplicated surgery, with a well-positioned implant and good central vision. It can occur with different lens materials and with both rounded and square optic edge designs. The symptom alone does not indicate a damaged implant, incorrect lens power or surgical error.
It is not confined to multifocal lenses. It can occur with a monofocal implant and can also be relevant after refractive lens exchange, which replaces the natural lens with an implant.
Will the shadow go away?
Many early cases become less noticeable or resolve over the following weeks or months. In one study of 320 cataract-operated eyes, 29 developed negative dysphotopsia. Of those 29, 24 had resolved within six weeks; five eyes had persistent symptoms, still reported at five years.
Some persistent shadows are tolerable; others affect confidence, concentration or everyday activities. An eye-chart result does not measure that burden. If symptoms persist, are worsening or remain troublesome, arrange a review rather than assuming that nothing can be done.
How is it assessed?
Assessment starts with the history: which eye is affected, when the shadow began, its position and whether it changes with lighting. The surgeon checks the cornea, implant and capsule, and examines the retina to exclude a tear, detachment or another explanation. Additional testing depends on the findings. There is no scan that proves negative dysphotopsia. Blocking the outer side of the eye, for example with a hand or a card held beside the temple, often makes the shadow fainter, and this can support the diagnosis.
Bring your implant details if available and mention any previous laser treatment to the capsule. A drawing of the shadow can help explain what you see.
What can help if it remains troublesome?
After other causes have been excluded, allowing time for healing and possible adaptation is reasonable for early or manageable symptoms. If the shadow persists and is sufficiently bothersome, the surgeon can discuss whether changing the implant–capsule arrangement is worth the risks. Treatment is individual.
Repositioning the optic in front of the capsule rim
With reverse optic capture, the central optic is brought in front of the opening in the anterior capsule while its haptics remain in the capsular bag. This changes the relationship between the optic edge and capsule rim. It requires suitable capsule support and geometry; it is not possible or appropriate in every eye.
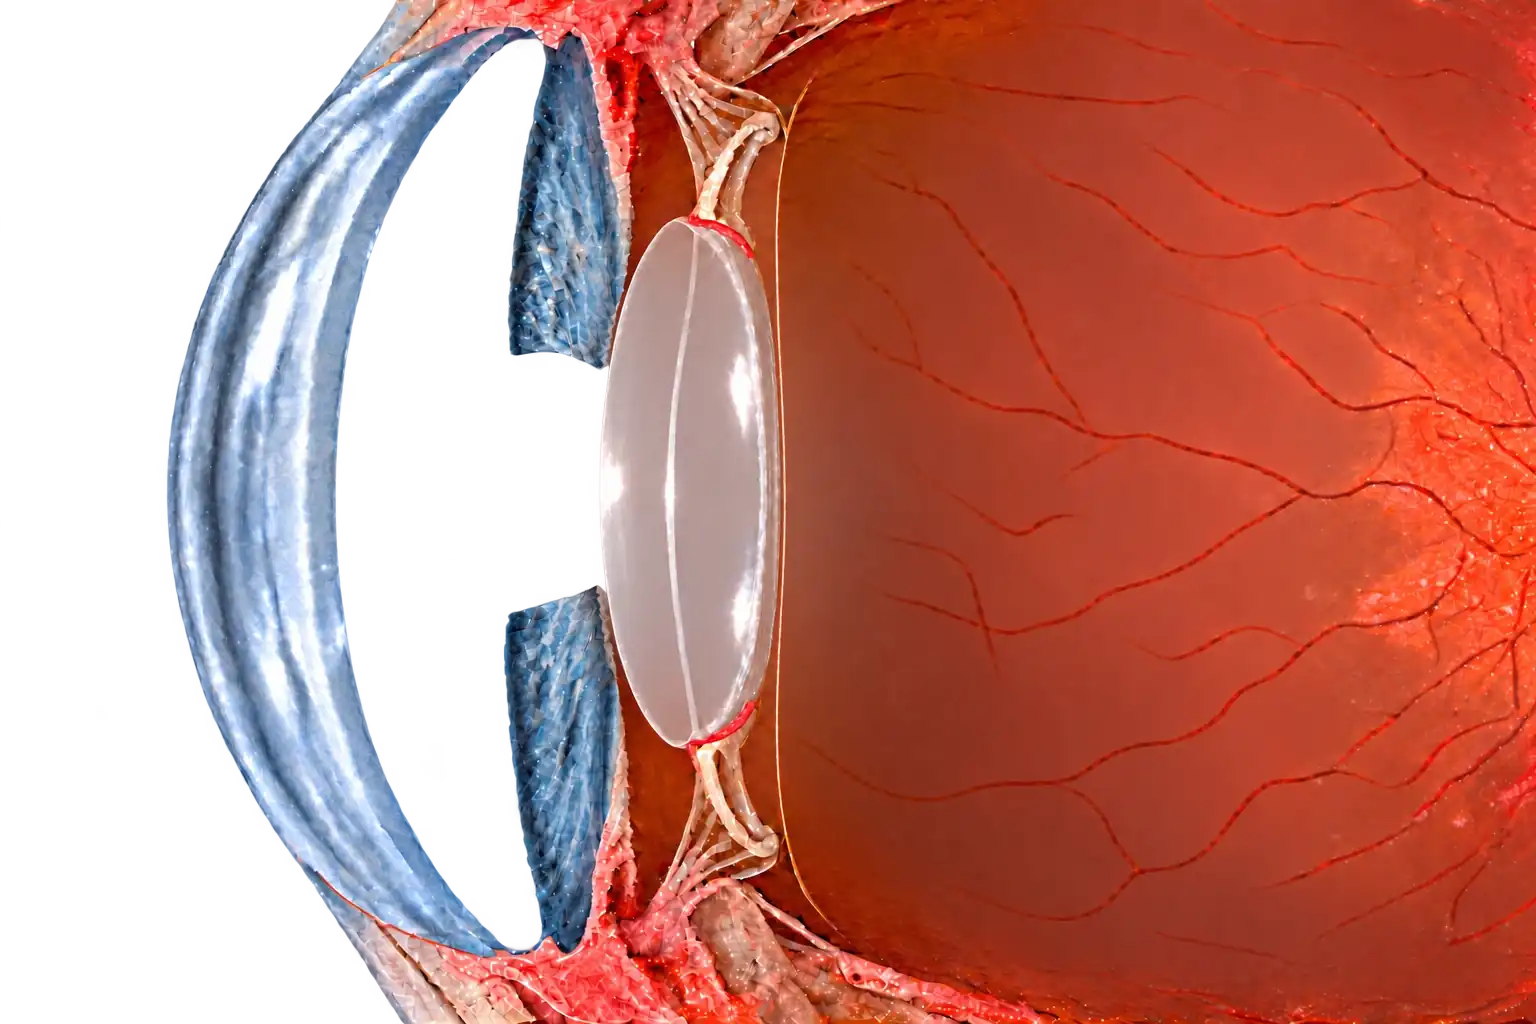
- Optic in front of the capsule opening
- Haptics remain inside the capsular bag
- Anterior capsule rim behind the optic
- Posterior capsule
The operation is done through small incisions, much like the original cataract surgery. The surgeon frees the optic from the capsule where needed and gently lifts it forward through the opening, so that the rim of the capsule sits behind the optic all the way round. The haptics (the implant's two supporting arms) stay in the capsular bag, which keeps the implant centred. Because the optic moves slightly forward, the focus can shift a little, and this is taken into account when planning.
Adding a supplementary lens
A suitable additional lens can sometimes be placed in the ciliary sulcus, the space behind the iris and in front of the capsule bag. It changes the peripheral optical arrangement without necessarily removing the original implant. Small studies report improvement in some patients, but symptoms can persist. The choice depends on the available space and the eye's anatomy.
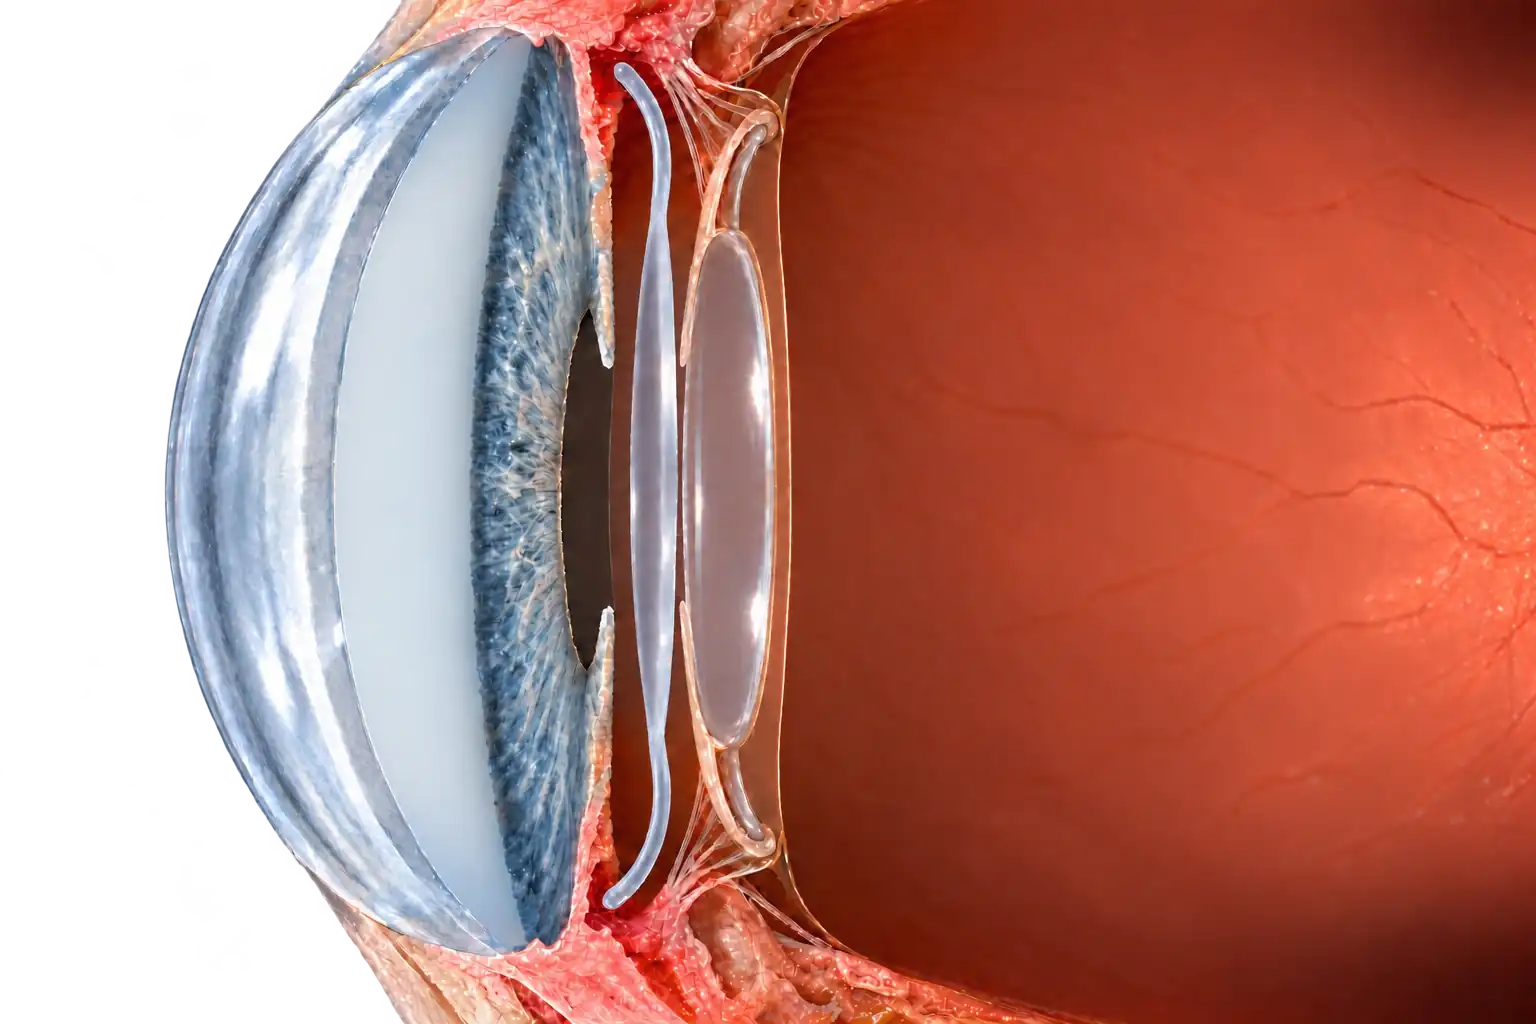
- Supplementary lens in front
- Supplementary haptics in the sulcus, behind the iris
- Original implant inside the capsular bag
- Posterior capsule
A supplementary lens is a thin implant designed to sit in front of an existing one. It is folded and inserted through a small incision, and its haptics rest in the sulcus, the angle behind the iris. The original implant stays where it is. Its power is usually low, and it can sometimes be chosen to fine-tune the glasses prescription at the same time. The video further down this page shows Dr Chen performing this operation.
Exchanging or otherwise repositioning the implant
Selected eyes may benefit from an implant exchange or a change in its position. Some implant designs may be less likely to cause negative dysphotopsia although substituting another lens in the same capsule position may not always solve the problem. Capsule support, previous surgery and the risks of further manipulation all influence the plan.
How do the options compare?
The options differ in what they change and what they require. Which one suits an eye depends on the examination, the implant and the capsule.
| Option | What it involves | Points to consider |
|---|---|---|
| Watching and waiting | Review over weeks to months while the eye heals and you adapt. | Many early shadows fade, and there is no surgical risk, but no guarantee the shadow will go. |
| Reverse optic capture | The optic is lifted in front of the capsule opening; the haptics stay in the bag. | Needs suitable capsule support. The focus may shift slightly. |
| Supplementary lens | A thin extra lens is placed in the sulcus, in front of the original implant. | The original implant stays in place. There must be enough room in front of it. |
| Exchanging or repositioning the implant | The implant is removed and replaced, or moved to a different position. | Swapping for another lens in the same position may not always help. It involves more handling of the eye. |
| YAG laser to the nasal front capsule | A laser trims a small part of the front capsule on the nasal side. | Evidence is limited. It is not the same as the routine laser for a cloudy capsule behind the implant. |
Further intraocular surgery has risks, including inflammation, pressure problems, iris irritation, retinal complications and, rarely, serious loss of vision. The likelihood and type of risk depend on the proposed operation and the eye. The potential benefit must justify those risks; improvement cannot be promised.
Is laser treatment an option?
In selected cases, removing a small part of the nasal anterior capsule with YAG laser has been described, but evidence is limited. This is different from the usual posterior YAG capsulotomy for a cloudy membrane behind the implant. Posterior capsulotomy is not a routine treatment for negative dysphotopsia and can make a later lens exchange more complex. The cause of the symptoms and any possible implant surgery should be discussed before proceeding.
What does supplementary lens surgery involve?
Dr Chen's video shows an additional lens being implanted for the treatment negative dysphotopsia.
Can negative dysphotopsia be prevented?
There is no method that reliably prevents every case. Proposed measures include changes to implant orientation and the relationship between the optic and anterior capsule. Certain monofocal intraocular lens designs may be associated with less risk of negative dysphotopsia.
If you experienced negative dysphotopsia in your first eye, tell your surgeon before surgery on the other eye so this can be considered in planning. Lens choice and positioning still need to meet the eye's other requirements.
What should I discuss at my review?
- Have retinal and other causes of the shadow been excluded?
- Does the pattern fit negative dysphotopsia, and is it changing with time?
- What are the advantages and disadvantages of further observation?
- If treatment is considered, why does that option suit my implant and capsule?
- Would any proposed laser procedure affect later surgical options?
For a non-urgent review, ask your treating ophthalmologist or arrange an assessment with Dr Simon Chen at Vision Eye Institute Chatswood. New or worsening shadows should follow the urgent-care advice above.
Where can I read more?
What does the evidence mean for clinicians?
The illumination-gap and capsule–optic hypotheses are complementary rather than necessarily competing explanations. The 2018 iris study measured 63 eyes but included only three symptomatic eyes from two patients.
In Masket and colleagues' retrospective series, secondary reverse optic capture improved symptoms in 21/22 eyes and supplementary implantation in 8/11, compared with 0/5 bag-to-bag exchanges. A separate supplementary-lens series reported complete resolution in 6/10 eyes, partial improvement in two and persistence in two.
Orientation evidence also requires care. A 2020 trial's four-week result (9/110 versus 18/110; RR 0.50, 95% CI 0.235–1.064; p=0.072) was not statistically conclusive. The 2022 trial found orientation-related differences at 4–6 weeks for its studied monofocal design. Neither establishes a universal strategy for preventing chronic ND.
What intraocular lenses do eye doctors choose for themselves?
References
- Holladay JT, Simpson MJ. Negative dysphotopsia: Causes and rationale for prevention and treatment. J Cataract Refract Surg. 2017;43:263–275. Study
- Simpson MJ, Muzyka-Woźniak M. Iris characteristics affecting far peripheral vision and negative dysphotopsia. J Cataract Refract Surg. 2018;44:459–465. Study
- Masket S, et al. Surgical management of negative dysphotopsia. J Cataract Refract Surg. 2018;44:6–16. Abstract
- Sharma P, Kalia S, Chouhan JK. Incidence and causes of negative dysphotopsia after uncomplicated cataract surgery – A randomized clinical trial. Indian J Ophthalmol. 2021;69:1786–1791. Full text
- Devgan U. Can we prevent negative dysphotopsia? Cataract Coach. 30 September 2018. Expert discussion
- Wanniarachchi K, et al. Management of positive and negative dysphotopsia postcataract surgery – A literature review. Taiwan J Ophthalmol. 2025;15:572–579. Review
- Simpson MJ, et al. Vignetting and peripheral double images with intraocular lenses. Biomed Opt Express. 2025;16:2495–2503. Full text
- Makhotkina NY, et al. Effect of supplementary implantation of a sulcus-fixated intraocular lens in patients with negative dysphotopsia. J Cataract Refract Surg. 2018;44:209–218. Abstract
- Manasseh GSL, et al. Pseudophakic negative dysphotopsia and intraocular lens orientation: a prospective double-masked randomized controlled trial. Acta Ophthalmol. 2020;98:e743–e746. Abstract
- Pamulapati SV, et al. Randomized controlled trial of intraocular lens orientation for dysphotopsia. Am J Ophthalmol. 2022;243:28–33. Abstract
- American Society of Retina Specialists. Retinal detachment. Patient information